


ICU Trials by ClinCalc analysis by Appwee
When I need to refresh my memory on a landmark intensive-care study, I do not always want to search through a browser, open several papers, and work out which result actually matters to the decision in front of me. That is the situation where ICU Trials makes sense. It is a paid medical app from ClinCalc LLC that gathers summaries of important critical-care trials in a compact reference designed for quick consultation.
I see it as a focused tool rather than a complete clinical information system. It will not replace a guideline, a primary paper, local policy, or experienced supervision. Its value is narrower and more practical: it helps me move from a clinical question to a recognizable trial summary without losing time to a broad web search. For students, residents, pharmacists, nurses, and clinicians revising intensive-care evidence, that focus can be useful.
From a clinical question to a usable trial summary
Starting with the problem rather than the app
The best way to use ICU Trials is to begin with a specific question. I might be wondering how a familiar intervention was tested, which patient group was studied, what the main comparison was, or why a particular result is still discussed in critical care. Opening the app with that question in mind makes the experience feel purposeful. Opening it without a topic can be less productive because a library of trial summaries is most helpful when I already know what I am trying to clarify.
That distinction matters. This is not an app that walks me through a patient assessment or generates a treatment plan. It is a reference for landmark critical-care research. I use it after identifying the subject, not as a substitute for identifying the subject. If a patient is deteriorating and I need immediate bedside guidance, I would prioritize the hospital’s approved resources and current clinical advice instead.
The app’s medical category and Everyone age rating make it approachable from a general access perspective, but the subject itself is specialized. A person without medical training may recognize the language but still struggle to judge how a trial applies to a real patient. The age label should not be confused with a promise that the content is suitable for unsupervised medical decisions.
Finding the relevant evidence
Once I have a topic, I use the app as a first-pass filter. A useful trial summary should help me orient myself quickly: what question the researchers asked, who was included, what intervention was compared, and what outcome shaped the study’s importance. That structure is more useful to me than a bare conclusion because it encourages the right next question: “Does this population resemble the patient or scenario I have in mind?”
One of the less obvious strengths of this format is that it supports recall. When I remember only a partial detail from a teaching session, a trial-focused reference can help reconnect the study name with its clinical theme. That is particularly handy before rounds, during exam preparation, or when discussing evidence with a colleague who remembers the result but not the design.
I also find it useful to separate three tasks that are easy to mix together. First, I identify the trial or subject. Second, I use the summary to reconstruct the broad clinical message. Third, I decide whether I need the original publication or a current guideline for confirmation. Keeping those steps separate prevents a concise summary from becoming an accidental replacement for deeper appraisal.
Reading the summary with the right level of skepticism
A short evidence summary is valuable because it reduces reading time, but compression always removes detail. I pay attention to the population, comparator, outcomes, and context instead of jumping straight to a headline result. A statistically interesting finding may have limited practical importance, and a result from one intensive-care population may not transfer neatly to another.
This is where I think the app works best as a conversation starter. It gives me a compact foundation for asking better questions: Was the intervention tested early or late? Were the patients selected in a way that differs from my setting? Was the outcome patient-centered, process-based, or a surrogate? Would current supportive care change the interpretation? Those questions are not a weakness of the app; they are the necessary next step after using any brief trial digest.
My main rule is simple: use the summary to locate the evidence, then use authoritative clinical sources to decide what to do. That workflow keeps the app useful without giving it more authority than a condensed reference should have.
Turning a quick lookup into a handoff
The handoff stage is where a reference app either becomes genuinely practical or remains a private reading tool. If I am preparing for rounds, I would not simply tell the team that an app says an intervention worked. I would carry forward the study question, the broad population, the comparison, and the limitation that matters most to the patient in front of us. The app can help me organize that explanation, but the clinical handoff still needs clear language and local context.
For teaching, I would use the same approach. A learner can look up a landmark study, explain its purpose in ordinary words, and then discuss why the result may or may not apply. That is more educational than memorizing an isolated conclusion. The workflow also helps reveal gaps: if I cannot explain who was studied or what the control group received, I know I need to read beyond the summary.
For pharmacists and nurses, the value may be different. They may use a trial summary to understand the evidence behind a treatment discussion, prepare a question for the prescriber, or connect a familiar bedside practice with the research that influenced it. The app does not remove the need to check dosing, contraindications, monitoring requirements, or institutional protocols. It simply gives the evidence conversation a more concrete starting point.
What the result looks like in everyday use
Imagine that I am reviewing a patient with severe illness and a colleague asks why the team is cautious about a commonly discussed intervention. I can use ICU Trials to revisit the landmark study associated with that topic, recover the basic design and clinical question, and then explain the evidence more accurately than I could from a vague memory. After that, I would check the current local guideline and the patient’s specific circumstances before drawing a conclusion.
Another realistic use is exam revision. Instead of reading an entire collection of papers in one sitting, I can work through trial summaries by theme, pause after each one, and write down the population, intervention, comparator, and key outcome in my own words. That turns the app into an active recall aid. The important trick is not to treat browsing as studying; I get more from it when I close the summary and try to reconstruct the study without looking.
It can also help before a journal-club discussion. I might use the app to refresh the historical landmark that led to a current practice, then move to the original paper for methods and detailed results. This two-stage process is faster than beginning with an unstructured search, while still respecting the difference between orientation and appraisal.
Where the workflow becomes less comfortable
The same focus that makes the app efficient can make it feel limited. A landmark-trial library is not the same as a continuously updated evidence platform, a drug reference, a calculator, or a guideline repository. If I need current recommendations, detailed safety information, patient-specific calculations, or a broad literature search, I would choose another resource first.
There is also a risk of false confidence. A polished summary can make a complex study feel settled even when its interpretation depends on selection criteria, changing standards of care, or outcomes that are difficult to translate to an individual patient. I would be especially careful when the app is being used by a learner who has not yet developed a habit of checking the original methods and newer evidence.
Another point of friction is the paid entry cost. ICU Trials is priced at $4.99, which is modest for a specialized reference but still worth considering if I only occasionally read critical-care research. Someone who already has access to a comprehensive institutional evidence service may find the extra purchase unnecessary. On the other hand, a learner who repeatedly revises landmark intensive-care trials may find the focused format easier to return to than a large general database.
Who should use it, and who should choose something else?
I would recommend ICU Trials to people who want a compact, trial-centered medical reference and already understand that summaries are the beginning of the evidence workflow. It is especially suitable for intensive-care learners, clinicians refreshing foundational studies, and anyone who needs a quick way to structure a discussion before consulting more detailed sources.
I would be more cautious about recommending it as a first medical app for a general audience. The content area is specialized, and the app’s purpose is not to translate research into individualized advice. A patient or caregiver looking for an explanation of a diagnosis would likely be better served by a patient-facing resource and direct communication with a healthcare professional.
I would also skip it if my main need is live clinical decision support. A current guideline service is a better choice when recommendations, contraindications, or local protocols are central. A primary-literature database is better when I need methods, subgroup analysis, confidence intervals, or the full discussion. ICU Trials sits between those options: faster and narrower than the literature, but less comprehensive and less directive than a clinical decision-support system.
Practical habits that improve the experience
I get better results when I treat each lookup as a small evidence exercise. Before opening a summary, I write down what I think the trial asked. After reading, I compare my assumption with the actual study question. This exposes a common problem in medical memory: remembering a trial’s conclusion while quietly changing the population or intervention it studied.
I also keep a short handoff note with four items: the clinical question, the studied population, the main comparison, and the reason the result may not transfer. That note is more useful than copying a conclusion because it preserves the boundaries around the evidence. It can support a teaching discussion without pretending that a historical trial answers every modern question.
A third useful habit is to pair the app with a date-aware source whenever the topic affects current care. Landmark trials remain important, but practice evolves. I use ICU Trials to understand the foundation, then check whether newer trials, updated guidance, or local policy changes the practical interpretation. This is the most important trade-off in using a concise reference: speed improves orientation, but currency and detail require additional checking.
Technical fit and long-term value
The app has been available since June 9, 2012, and its current version is 2026.07. It supports devices running iOS or Android version 8.0 or later, which gives it a broad compatibility range for people using older supported devices. ClinCalc LLC is the developer, and the app has passed the point where it feels like an untested niche download: it has more than ten thousand installs, a 4.6 average from over two hundred ratings, and sixteen written reviews.
Those figures suggest a small but established audience rather than a mass-market medical platform. I would interpret that appropriately. The app’s appeal is its specialization, not the breadth of a general health service. Its price also reinforces that positioning: it is a focused paid reference, so I expect to use it repeatedly rather than install it for a single question and forget it.
For long-term value, the key question is whether landmark critical-care trials appear often enough in my work or study routine. If they do, the quick-reference approach can save repeated searching and help organize revision. If I rarely deal with intensive-care evidence, a broader medical reference may provide more value per purchase, even if it is less convenient for this particular subject.
My final assessment after following the full workflow
ICU Trials succeeds when the starting condition is a focused question about a major critical-care study. It helps me move from uncertainty to orientation, then from orientation to a better handoff with colleagues or learners. The outcome is not a treatment decision generated by the app; it is a clearer understanding of what evidence I should examine next and how to discuss it responsibly.
I like its disciplined scope. It does not try to be a general medical encyclopedia, and that makes it easier to approach when I need trial context quickly. At the same time, that scope creates the main limitation: it cannot replace current guidelines, primary papers, institutional protocols, or patient-specific judgment. The workflow breaks when I expect a concise summary to answer questions it was never designed to answer.
For me, the purchase makes sense if I regularly study or discuss intensive-care evidence and want a portable reference for landmark trials. I would recommend it to a medically literate friend with that exact need, while reminding them to verify any decision that affects care in a current, authoritative source. Used that way, ICU Trials is a practical evidence primer: not the final destination, but a useful first stop before the more demanding work begins.
Gallery
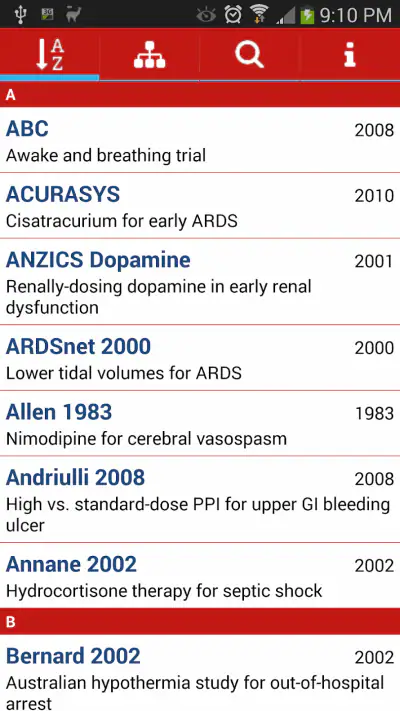
ICU Trials by ClinCalc Pros and Cons
- Quick access to evidence-based ICU clinical trial information
- Useful for checking landmark studies during bedside decision-making
- Search and browsing tools make specific trials easy to locate
- Covers major critical care topics in a focused
- specialized app
- Helpful reference for clinicians
- trainees
- and medical students
- Content may require clinical knowledge to interpret correctly
- Trial summaries may not include every recently published ICU study
- No substitute for full-text articles or institutional treatment protocols
- Some users may find the interface dated or visually basic
- Availability and features may vary between Android and iOS versions
ICU Trials by ClinCalc Frequently Asked Questions
What is ICU Trials by ClinCalc used for?
ICU Trials by ClinCalc is a medical reference app designed to help healthcare professionals quickly review landmark randomized controlled trials and major evidence related to critical care. It organizes studies by clinical topic and provides concise summaries of trial objectives, patient populations, interventions, outcomes, and conclusions. It is primarily an educational and decision-support resource, not a replacement for clinical judgment, institutional protocols, or current guidelines.
Who can benefit from using ICU Trials by ClinCalc?
The app is mainly intended for physicians, pharmacists, nurses, residents, medical students, and other healthcare professionals involved in intensive care or emergency medicine. It can also be useful for learners preparing for exams or reviewing evidence-based critical care practice. Because the summaries are clinically focused and may include medical terminology, users without healthcare training may find the content difficult to interpret without additional explanation.
Does ICU Trials by ClinCalc provide complete research papers or only summaries?
ICU Trials generally functions as a quick-reference library rather than a full-text journal database. Its value comes from presenting important critical-care trials in a compact, readable format, allowing users to review the key question, study design, findings, and practical implications without searching through lengthy publications. Anyone making a treatment decision should consult the original paper, supplementary data, updated reviews, and applicable guidelines for complete context.
Can the information in ICU Trials be used to make treatment decisions?
The app can support evidence-based discussion and help clinicians recall influential studies, but it should not be used as the sole basis for diagnosing or treating a patient. Clinical evidence may have limitations, populations and protocols can differ, and recommendations may change as new research becomes available. Always consider the individual patient, local policies, contraindications, current professional guidance, and advice from a qualified healthcare team before acting.
Does ICU Trials by ClinCalc require an internet connection or include any special features?
Availability of specific functions may depend on the version of the app and the platform on which it is installed. Users should check the current store listing for information about offline access, updates, pricing, advertisements, and supported devices. In general, it is best viewed as a focused reference tool for browsing critical-care trial summaries, with usefulness depending on how regularly its content is maintained and updated.














